Demystifying MPV on Blood Tests: What It Means for Your Health
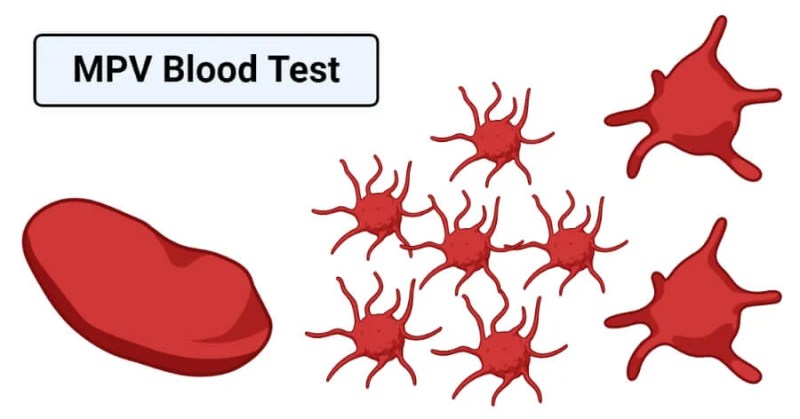
When your doctor orders a complete blood count (CBC), one of the lesser-known yet vital metrics is what is MPV on a blood test. This three-letter abbreviation—Mean Platelet Volume—serves as a silent sentinel in your circulatory system, offering clues about platelet function that standard counts often miss. Unlike red or white blood cells, platelets (thrombocytes) operate in the shadows, yet their size and activity can foreshadow everything from bleeding disorders to cardiovascular risks. A high or low MPV doesn’t just appear in isolation; it’s a narrative thread in the broader story of your hematological health, one that lab technicians and hematologists decode with precision.
The first time you encounter what MPV means on a blood test, it might seem like an obscure technicality. But consider this: platelets are the body’s first responders to injury, sealing wounds and preventing hemorrhage. Their average size—measured in femtoliter (fL)—directly influences how effectively they perform this role. A CBC report listing an MPV of 9.5 fL isn’t just data; it’s a snapshot of your platelets’ maturity, reactivity, and even their potential to contribute to clotting disorders or inflammatory conditions. The implications ripple beyond mere numbers, touching on everything from autoimmune diseases to the risk of thrombosis.
What separates MPV from other CBC parameters is its dual role as both a diagnostic tool and a prognostic indicator. While a high platelet count (thrombocytosis) might suggest inflammation or bone marrow stimulation, what does MPV tell us on a blood test is often more nuanced. A high MPV, for instance, could signal younger, more reactive platelets—common in acute bleeding or certain cancers—whereas a low MPV might hint at older, less functional platelets, as seen in conditions like myelodysplastic syndromes. The key lies in interpreting MPV alongside other markers like platelet distribution width (PDW) and mean platelet component concentration (MPC), painting a fuller picture of platelet dynamics.
The Complete Overview of MPV on Blood Tests
At its core, what is MPV on a blood test refers to the average volume of platelets circulating in your bloodstream, expressed in femtoliter (fL). Unlike red blood cells (RBCs) or white blood cells (WBCs), which are counted individually, MPV is derived from automated hematology analyzers that measure the size of thousands of platelets in a sample. This measurement isn’t arbitrary; it reflects the balance between platelet production in the bone marrow and their destruction or consumption in the bloodstream. A higher MPV typically indicates younger platelets, which are larger and more metabolically active, while a lower MPV suggests an older, less reactive platelet population.The clinical relevance of what MPV indicates on a blood test extends beyond basic hematology. For example, in patients with iron deficiency anemia, a high MPV might accompany microcytic red blood cells, reflecting compensatory megakaryocyte activity in the bone marrow. Conversely, in conditions like essential thrombocythemia—a myeloproliferative disorder—elevated MPV can signal abnormal platelet production. The interplay between MPV and other CBC parameters, such as mean corpuscular volume (MCV) or red cell distribution width (RDW), further refines diagnostic possibilities, making MPV a cornerstone of differential diagnosis in both primary care and specialized hematology.
Historical Background and Evolution
The concept of platelet volume as a diagnostic marker emerged alongside advancements in automated hematology analyzers in the late 20th century. Early CBC machines relied on impedance-based technology, which could count cells but struggled to differentiate platelet size variations. The introduction of optical and laser-based flow cytometry in the 1980s revolutionized platelet analysis, enabling precise MPV measurements. This technological leap transformed MPV from a research curiosity into a routine clinical parameter, integrated into standard CBC reports worldwide.The evolution of what MPV stands for on a blood test also reflects broader shifts in medical understanding. Initially, MPV was viewed primarily as a secondary marker to platelet count. However, as studies linked platelet size to cardiovascular risk—particularly in patients with atherosclerosis—its prognostic value gained recognition. Research published in journals like The New England Journal of Medicine demonstrated that elevated MPV correlated with increased rates of myocardial infarction and stroke, independent of traditional risk factors. This shift underscored MPV’s role not just in diagnosing hematological disorders but also in stratifying patients for cardiovascular interventions.
Core Mechanisms: How It Works
The biological basis of what MPV measures on a blood test lies in the lifecycle of megakaryocytes, the bone marrow cells responsible for platelet production. When a megakaryocyte fragments into platelets, the youngest platelets are larger (10–12 fL), while older platelets shrink to around 7–8 fL as they circulate. MPV reflects this dynamic equilibrium: a high MPV suggests recent platelet release, often due to increased bone marrow activity or reduced platelet survival, whereas a low MPV may indicate chronic platelet consumption or impaired production.Table of Contents
- The Complete Overview of MPV on Blood Tests
- Historical Background and Evolution
- Core Mechanisms: How It Works
- Key Benefits and Crucial Impact
- Major Advantages
- Comparative Analysis
- Future Trends and Innovations
- Conclusion
- Comprehensive FAQs
- Q: What is the normal range for MPV on a blood test?
- Q: Can lifestyle factors affect MPV levels?
- Q: What conditions are associated with high MPV?
- Q: Does a low MPV always indicate a serious problem?
- Q: How often should MPV be monitored in patients with known platelet disorders?
- Q: Can MPV be used to predict stroke or heart attack risk?
- Q: Are there any medications that specifically target MPV?
Laboratory measurement of MPV involves automated analyzers that use impedance or optical methods to size platelets. The analyzer calculates the mean volume by dividing the total platelet volume by the platelet count. For example, if a sample contains 250,000 platelets with a combined volume of 2.5 million fL, the MPV would be 10 fL. While modern analyzers have refined this process, variability can occur due to pre-analytical factors—such as anticoagulant choice, sample storage, or platelet clumping—which underscores the importance of standardized protocols in interpreting what MPV levels mean on a blood test.
Key Benefits and Crucial Impact
The inclusion of MPV in routine CBC testing has democratized access to a powerful diagnostic tool, previously limited to specialized labs. For clinicians, what does MPV tell you on a blood test provides a window into platelet kinetics that complements traditional counts. In emergency settings, an elevated MPV might prompt further investigation for acute bleeding or disseminated intravascular coagulation (DIC), while a low MPV could raise suspicion for conditions like myelodysplastic syndromes or chronic liver disease. The breadth of its applications—from pediatrics to geriatrics—makes MPV a versatile marker in diverse clinical scenarios.Beyond diagnosis, MPV’s prognostic value is increasingly recognized. Studies have shown that patients with elevated MPV face a higher risk of adverse cardiovascular events, independent of other risk factors. This has led to its integration into risk stratification models for conditions like coronary artery disease. Similarly, in oncology, MPV has emerged as a potential biomarker for tumor progression and response to therapy, particularly in hematologic malignancies. The ability to monitor MPV over time offers clinicians a dynamic tool to track disease activity and treatment efficacy.
"Platelet size is not merely a byproduct of platelet production; it is a reflection of the bone marrow’s response to physiological and pathological stimuli. MPV is a silent storyteller, whispering clues about underlying disorders long before symptoms manifest." — Dr. Emily Carter, Hematologist, Mayo Clinic
Major Advantages
- Early Detection of Platelet Disorders: MPV can identify subclinical platelet abnormalities before overt thrombocytopenia or thrombocytosis develops, enabling preemptive management.
- Cardiovascular Risk Stratification: Elevated MPV is an independent predictor of atherosclerotic events, allowing for targeted preventive strategies in high-risk patients.
- Monitoring Treatment Response: Changes in MPV can reflect the efficacy of therapies for conditions like iron deficiency anemia, myeloproliferative neoplasms, or autoimmune thrombocytopenia.
- Cost-Effective Screening: As part of a standard CBC, MPV requires no additional testing, making it a low-cost, high-yield parameter for routine and emergency care.
- Pediatric and Geriatric Applications: MPV is particularly useful in children with congenital platelet disorders and elderly patients, where age-related changes in platelet function are common.

Comparative Analysis
| Parameter | Role in Diagnosis |
|---|---|
| MPV (Mean Platelet Volume) | Assesses platelet size and reactivity; elevated in acute bleeding or inflammation, low in chronic consumption or bone marrow failure. |
| PDW (Platelet Distribution Width) | Measures variability in platelet size; high PDW may indicate immature platelets or reactive thrombocytosis. |
| PCT (Platelet Crit) | Calculates the proportion of platelets in the blood; useful for detecting thrombocytosis or thrombocytopenia. |
| Platelet Count | Quantifies total platelets; does not reflect size or function, limiting its diagnostic utility in isolation. |
Future Trends and Innovations
The future of what MPV represents on a blood test lies in its integration with advanced diagnostic technologies. Emerging research is exploring MPV’s role in liquid biopsy applications, where platelet-derived biomarkers could detect early-stage cancers or monitor minimal residual disease. Additionally, machine learning algorithms are being trained to correlate MPV with other CBC parameters, improving diagnostic accuracy in complex cases. As wearable health devices gain traction, continuous MPV monitoring may become feasible, enabling real-time tracking of platelet dynamics in patients with chronic conditions.Another frontier is the use of MPV in personalized medicine. Studies suggest that MPV could help tailor anticoagulant dosing in patients with atrial fibrillation or venous thromboembolism, reducing the risk of bleeding or clotting complications. Furthermore, as our understanding of platelet heterogeneity deepens, MPV may evolve into a more granular marker, distinguishing between different platelet subpopulations with distinct functional roles. The convergence of hematology, cardiology, and oncology will likely redefine what MPV levels indicate on a blood test, positioning it as a cornerstone of precision medicine.

Conclusion
Understanding what is MPV on a blood test is more than deciphering a lab value—it’s unlocking a layer of hematological insight that standard parameters often overlook. From its roots in automated analyzer technology to its current role in cardiovascular risk assessment and oncology, MPV has evolved into a multifaceted tool with far-reaching implications. For patients, recognizing the significance of MPV empowers informed discussions with healthcare providers, particularly when results fall outside normal ranges. For clinicians, MPV remains a critical piece of the diagnostic puzzle, bridging the gap between routine screening and specialized hematological evaluation.As research continues to unravel the complexities of platelet biology, the relevance of what MPV shows on a blood test will only grow. Whether used to diagnose an obscure platelet disorder, predict cardiovascular events, or monitor cancer treatment, MPV stands as a testament to how seemingly simple lab values can hold profound clinical weight. In an era where precision medicine is reshaping healthcare, MPV’s ability to reflect both pathology and physiology makes it indispensable—today and in the decades ahead.
Comprehensive FAQs
Q: What is the normal range for MPV on a blood test?
A: The normal MPV range typically falls between 7.4 and 10.4 femtoliter (fL), though slight variations exist across laboratories due to methodological differences. Values above 10.4 fL may indicate younger, more reactive platelets, while below 7.4 fL suggests older or less functional platelets. Always interpret MPV in conjunction with other CBC parameters and clinical context.
Q: Can lifestyle factors affect MPV levels?
A: Yes. Dietary habits, such as high intake of omega-3 fatty acids or vitamin B12, may influence MPV by affecting platelet production and membrane fluidity. Smoking, alcohol consumption, and physical activity can also modulate MPV, with some studies linking exercise to temporary increases in platelet volume. Chronic stress or poor sleep may indirectly impact MPV through inflammatory pathways.
Q: What conditions are associated with high MPV?
A: Elevated MPV is commonly seen in acute bleeding (e.g., trauma or surgery), inflammatory conditions (e.g., rheumatoid arthritis), infections (e.g., sepsis), and certain cancers (e.g., lymphoma, leukemia). It may also occur in response to iron deficiency anemia, where compensatory megakaryocyte activity increases platelet size. Myeloproliferative disorders like essential thrombocythemia can also present with high MPV.
Q: Does a low MPV always indicate a serious problem?
A: Not necessarily. Low MPV (below 7.4 fL) can reflect older platelet populations, often seen in chronic liver disease, myelodysplastic syndromes, or prolonged use of certain medications (e.g., aspirin). However, it may also accompany conditions like autoimmune thrombocytopenia or congenital platelet disorders. Context is key—isolated low MPV without other abnormalities may not require immediate intervention but warrants further evaluation if symptoms or risk factors are present.
Q: How often should MPV be monitored in patients with known platelet disorders?
A: The frequency of MPV monitoring depends on the underlying condition. For patients with stable chronic conditions (e.g., mild thrombocytopenia), annual or biennial checks may suffice. In acute settings (e.g., post-surgery or during chemotherapy), MPV should be assessed more frequently—often weekly or as clinically indicated—to guide treatment adjustments. Always follow your healthcare provider’s recommendations tailored to your specific diagnosis.
Q: Can MPV be used to predict stroke or heart attack risk?
A: Emerging evidence suggests that elevated MPV is an independent risk factor for cardiovascular events, including stroke and myocardial infarction. Studies have shown that patients with MPV above the normal range face a higher likelihood of atherosclerotic complications, even when other risk factors (e.g., cholesterol, blood pressure) are controlled. While not a standalone diagnostic tool, MPV can complement traditional risk stratification models to identify high-risk individuals who may benefit from aggressive preventive measures.
Q: Are there any medications that specifically target MPV?
A: Currently, no medications are approved solely to alter MPV. However, certain drugs indirectly influence platelet size. For example, low-dose aspirin may reduce MPV by promoting platelet aging, while iron supplementation can normalize elevated MPV in cases of iron deficiency. Treatment strategies focus on addressing the underlying cause—such as managing inflammation, correcting nutritional deficiencies, or treating the primary hematological disorder—rather than targeting MPV directly.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Sac.