Understanding What Is a WBC Lab Test: The Definitive Breakdown
When a doctor orders a complete blood count (CBC), one of the most critical metrics they examine is the white blood cell (WBC) count—a silent sentinel of the body’s defenses. This single number, derived from a WBC lab test, can reveal hidden battles against infection, chronic inflammation, or even early signs of blood disorders. Unlike other lab values that fluctuate subtly, WBC levels can swing dramatically overnight, signaling emergencies like sepsis or subtler shifts in immune health. Yet for many patients, the term "what is a WBC lab test" remains shrouded in ambiguity: Is it just another routine check, or does it hold the key to diagnosing conditions before symptoms appear?
The WBC lab test isn’t a monolithic measurement—it’s a sophisticated breakdown of five distinct cell types, each with its own role in immunity. Neutrophils rush to bacterial threats; lymphocytes mount viral defenses; eosinophils combat parasites. A single blood draw can expose imbalances in this cellular orchestra, offering clues to everything from allergies to leukemia. But the test’s power lies in its context: A high WBC count (leukocytosis) might indicate infection, stress, or malignancy, while a low count (leukopenia) could signal immune suppression. The challenge? Interpreting these results requires understanding not just the numbers, but the patient’s medical history, medication use, and even lifestyle factors like sleep or diet.
What separates a WBC lab test from other diagnostic tools is its dual nature—as both a screening tool and a red flag. In emergency rooms, it’s the first line of defense; in oncology clinics, it’s a biomarker for remission or relapse. Yet despite its ubiquity, misconceptions persist. Some dismiss it as "just another blood test," while others fear abnormal results without grasping their nuanced meanings. This article dismantles those assumptions, exploring the science, clinical applications, and evolving role of the WBC lab test in modern medicine.
The Complete Overview of What Is a WBC Lab Test
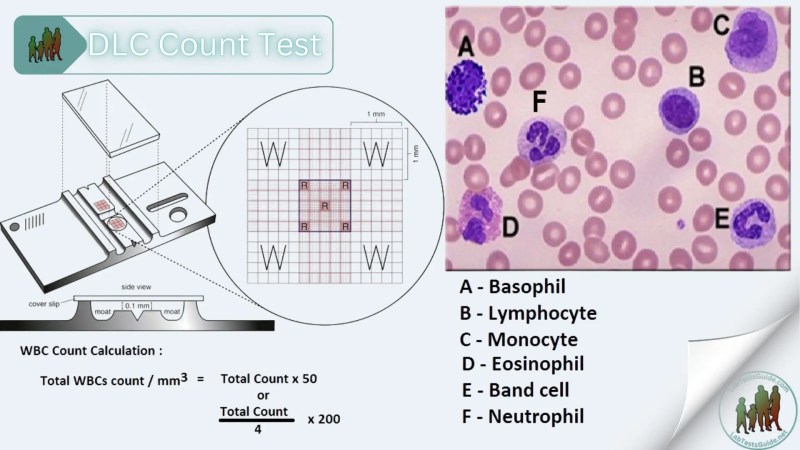
The WBC lab test is a foundational component of hematological assessment, measuring the concentration and differential distribution of white blood cells in peripheral blood. Unlike red blood cells, which transport oxygen, WBCs are the body’s mobile immune system—patrolling tissues, identifying pathogens, and coordinating responses. The test is typically performed as part of a complete blood count (CBC), though standalone WBC panels exist for targeted monitoring (e.g., in oncology or infectious disease). Results are reported in cells per microliter (cells/µL), with normal ranges varying slightly by lab (e.g., 4,500–11,000 cells/µL for adults), but pediatric and geriatric ranges differ due to developmental and age-related immune changes.The test’s clinical utility stems from its ability to reflect systemic inflammation, infection, or hematologic disorders. For example, a WBC lab test might reveal neutrophilia (elevated neutrophils) in bacterial pneumonia or lymphocytosis (high lymphocytes) in chronic viral infections like mononucleosis. Conversely, leukopenia (low WBCs) could indicate bone marrow suppression from chemotherapy or autoimmune destruction. The differential count—breaking down WBCs into neutrophils, lymphocytes, monocytes, eosinophils, and basophils—adds layers of diagnostic precision. This granularity is why clinicians often say the WBC lab test is "the first biopsy of the immune system."
Historical Background and Evolution
The origins of the WBC lab test trace back to the 19th century, when early microscopists like Paul Ehrlich and Ilya Mechnikov pioneered the study of immune cells. Ehrlich’s staining techniques (1880s) allowed visualization of WBCs, while Mechnikov’s work on phagocytosis laid the groundwork for understanding their function. However, it wasn’t until the mid-20th century that automated hematology analyzers—like the Coulter Counter (1950s)—revolutionized the WBC lab test by replacing manual cell counting with electronic precision. This shift reduced human error and enabled faster turnaround times, critical for acute care settings.Today’s WBC lab tests leverage advanced flow cytometry and laser-based analyzers, capable of distinguishing not just cell types but also immature forms (e.g., blasts in leukemia). The integration of differential WBC counts into routine CBCs transformed the test from a broad screening tool into a diagnostic powerhouse. Historically, abnormal results might have led to invasive procedures (e.g., bone marrow biopsies), but modern WBC lab tests now often obviate such steps, guiding targeted therapies with minimal intervention. This evolution reflects a broader trend in medicine: using non-invasive, high-throughput lab tests to replace riskier diagnostic methods.
Core Mechanisms: How It Works
The WBC lab test begins with a venous blood draw, typically from the arm, though capillary samples (finger pricks) are used in pediatric or point-of-care settings. The blood is mixed with an anticoagulant (e.g., EDTA) to prevent clotting, then processed in an automated analyzer. These machines use hydrodynamic focusing—a technique where blood is forced through a narrow channel, allowing lasers to detect and classify cells based on size, granularity, and internal complexity. For the differential count, a second phase employs cytochemical stains (e.g., Wright-Giemsa) or flow cytometry, which sorts cells into their five subtypes by binding to surface markers.Table of Contents
- The Complete Overview of What Is a WBC Lab Test
- Historical Background and Evolution
- Core Mechanisms: How It Works
- Key Benefits and Crucial Impact
- Major Advantages
- Comparative Analysis
- Future Trends and Innovations
- Conclusion
- Comprehensive FAQs
- Q: What does it mean if my WBC count is high?
- Q: Can lifestyle factors affect my WBC lab test results?
- Q: Is a low WBC count always dangerous?
- Q: Why do I need a differential WBC count if the total WBC is normal?
- Q: How often should I get a WBC lab test if I’m healthy?
- Q: Can a WBC lab test detect cancer early?
- Q: What should I do if my WBC lab test results are abnormal?
- Q: Are there any natural ways to improve my WBC count?
- Q: How accurate are home WBC testing devices?
The analytical process isn’t flawless: WBC lab tests can be skewed by hemolysis (red blood cell breakdown), lipemia (high fat levels), or icterus (elevated bilirubin), requiring lab technicians to flag and correct such interferences. False elevations in WBC counts can also occur due to stress leukocytosis (e.g., from vigorous exercise or emotional distress), a phenomenon known as the "fight-or-flight" response. Conversely, pseudoleukopenia may arise from platelet clumping or poor sample handling. These nuances underscore why WBC lab tests must be interpreted in conjunction with clinical correlation—no number exists in isolation.
Key Benefits and Crucial Impact
The WBC lab test occupies a unique position in clinical diagnostics: it’s both a screening tool and a diagnostic trigger. In primary care, it’s the first line of defense against undiagnosed infections, autoimmune diseases, or hematologic malignancies. A patient presenting with fever and a WBC count of 20,000 cells/µL might avoid unnecessary imaging if the differential reveals neutrophilia pointing to bacterial sepsis. In oncology, WBC lab tests monitor treatment efficacy—e.g., a rising lymphocyte count post-chemotherapy may signal immune recovery. Even in non-medical contexts, the test informs public health responses, such as tracking community-wide leukocytosis during outbreaks.The test’s impact extends beyond individual patients. In resource-limited settings, WBC lab tests serve as a low-cost, high-yield diagnostic, reducing reliance on expensive imaging or biopsies. For example, in sub-Saharan Africa, WBC lab tests help differentiate malaria (often with lymphopenia) from typhoid fever (associated with leukocytosis). This scalability makes the WBC lab test a cornerstone of global health initiatives. As one hematologist noted:
"The white blood cell count is the canary in the coal mine of systemic illness. It doesn’t just tell you there’s a problem—it often tells you what kind of problem it is, and where to look next." —Dr. Emily Carter, Chief of Hematopathology, Johns Hopkins Hospital
Major Advantages
- Rapid turnaround: Results are typically available within hours, enabling urgent clinical decisions (e.g., antibiotic initiation for suspected sepsis).
- Non-invasive: Requires only a blood draw, eliminating patient discomfort associated with biopsies or imaging.
- Multidimensional insights: The differential count provides a "fingerprint" of immune activity, distinguishing viral (lymphocyte-predominant) from bacterial (neutrophil-predominant) infections.
- Cost-effective: As part of a CBC, the test costs under $50 USD, making it accessible even in low-resource settings.
- Monitoring tool: Serial WBC lab tests track treatment responses (e.g., in HIV or cancer), allowing adjustments before symptoms worsen.

Comparative Analysis
While the WBC lab test is indispensable, other diagnostic tools complement or replace it in specific scenarios. Below is a comparison of key tests used to assess immune function or infection:| Test | Purpose |
|---|---|
| WBC Lab Test (CBC with Differential) | Broad immune assessment; detects infections, inflammation, or hematologic disorders. Ideal for acute or chronic monitoring. |
| CRP (C-Reactive Protein) | Measures acute inflammation (e.g., post-surgery or infection). Less specific than WBCs but faster for inflammatory trends. |
| ESR (Erythrocyte Sedimentation Rate) | Indirect marker of inflammation (elevated in autoimmune diseases). Slower than CRP/WBC but useful for long-term monitoring. |
| Flow Cytometry (Immunophenotyping) | Advanced analysis of WBC subsets (e.g., identifying leukemia subtypes). More precise but costly and time-consuming. |
Future Trends and Innovations
The WBC lab test is poised for transformation through artificial intelligence (AI) and point-of-care (POC) diagnostics. Current analyzers use rule-based algorithms to flag abnormal results, but AI models are now being trained to predict clinical outcomes from WBC patterns—e.g., identifying sepsis risk hours before symptoms manifest. Meanwhile, POC WBC tests (e.g., handheld devices like the Abbott i-STAT) are expanding access in rural or disaster settings, where lab infrastructure is limited. Another frontier is liquid biopsy technology, which may one day detect WBC abnormalities in blood plasma without traditional cell counting, offering earlier cancer detection.Beyond technology, the WBC lab test’s role in personalized medicine is growing. Researchers are exploring how baseline WBC profiles correlate with drug responses (e.g., neutropenia risk from chemotherapy) or chronic disease progression (e.g., lymphocytosis in rheumatoid arthritis). As genomics integrates with hematology, WBC lab tests may soon include genetic markers (e.g., mutations in leukemia) alongside traditional counts. The future of the test lies not just in accuracy, but in contextual intelligence—using WBC data to tailor therapies before symptoms dictate the course.

Conclusion
The WBC lab test is more than a routine procedure; it’s a window into the body’s hidden battles. From its 19th-century roots to today’s AI-driven analyzers, its evolution mirrors advances in immunology and diagnostic precision. Yet its power lies not in complexity, but in simplicity: a few drops of blood can reveal whether the immune system is overwhelmed, suppressed, or primed for action. For patients, understanding what is a WBC lab test demystifies a critical diagnostic tool, empowering them to ask informed questions about abnormal results. For clinicians, it remains the first—and often last—test needed to guide lifesaving decisions.As medicine shifts toward predictive and preventive care, the WBC lab test will continue to adapt, blending tradition with innovation. Whether in a bustling ER or a remote clinic, its ability to illuminate the unseen ensures it will remain a staple of medical practice for decades to come.
Comprehensive FAQs
Q: What does it mean if my WBC count is high?
A: A high WBC count (leukocytosis) typically indicates an infection, inflammation, or stress response. Common causes include bacterial infections (e.g., pneumonia), viral illnesses (e.g., flu), or physical stress (e.g., intense exercise). However, conditions like leukemia or chronic inflammation (e.g., rheumatoid arthritis) can also elevate WBCs. Always correlate with clinical symptoms and other lab tests.
Q: Can lifestyle factors affect my WBC lab test results?
A: Yes. Stress leukocytosis (temporary WBC elevation) can occur due to emotional distress, sleep deprivation, or intense physical activity. Caffeine, smoking, and even time of day (WBCs often peak in the evening) may influence results. Fasting or dehydration can also skew counts. Inform your doctor if you’ve experienced recent stress or lifestyle changes before interpreting the test.
Q: Is a low WBC count always dangerous?
A: Not necessarily. Leukopenia (low WBCs) can be benign in some cases (e.g., during pregnancy or in athletes with low baseline counts). However, it often signals immune suppression from medications (e.g., chemotherapy), viral infections (e.g., HIV), or autoimmune diseases (e.g., lupus). If accompanied by fever or infections, it requires prompt medical evaluation to prevent complications like sepsis.
Q: Why do I need a differential WBC count if the total WBC is normal?
A: A normal total WBC count doesn’t rule out underlying issues. The differential count reveals imbalances in specific cell types—e.g., high eosinophils might indicate allergies or parasites, while low lymphocytes could signal HIV or chronic stress. Even with a normal total, the differential can guide targeted treatments (e.g., steroids for eosinophilic disorders).
Q: How often should I get a WBC lab test if I’m healthy?
A: Routine WBC lab tests aren’t recommended for healthy individuals without symptoms. They’re typically ordered during annual physicals only if risk factors (e.g., family history of blood disorders) exist. For most people, the test’s value lies in its reactive use—when symptoms (fever, fatigue, infections) prompt evaluation. Overtesting can lead to unnecessary anxiety or misdiagnoses.
Q: Can a WBC lab test detect cancer early?
A: While abnormal WBC patterns (e.g., persistent lymphocytosis or blast cells) can signal hematologic cancers like leukemia or lymphoma, the test isn’t a definitive screening tool. Early-stage cancers often present with normal WBCs. However, serial monitoring of WBCs and differentials is critical in oncology to detect relapses or treatment side effects (e.g., chemotherapy-induced neutropenia).
Q: What should I do if my WBC lab test results are abnormal?
A: Don’t panic, but act promptly. Abnormal results should be discussed with your doctor, who will consider your medical history, symptoms, and other tests. Follow-up may include repeat testing, imaging, or specialist referrals (e.g., infectious disease or hematology). Keeping a symptom diary (e.g., fever, fatigue) can help contextualize the results.
Q: Are there any natural ways to improve my WBC count?
A: For leukopenia caused by lifestyle or mild infections, lifestyle adjustments may help: Ensure adequate vitamin B12, folate, and zinc intake (found in leafy greens, nuts, and lean meats). Avoid smoking and limit alcohol. Probiotics (e.g., yogurt) may support immune function, but severe deficiencies require medical treatment. Never self-medicate—consult a doctor before taking supplements, especially if you’re on immunosuppressants.
Q: How accurate are home WBC testing devices?
A: Home devices (e.g., finger-prick tests like the HemaApp) offer preliminary WBC estimates but lack the precision of lab analyzers. They’re useful for trending (e.g., monitoring chronic conditions) but shouldn’t replace clinical testing for diagnosis. False readings can occur due to user error or sample contamination. Always confirm abnormal results with a professional WBC lab test.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Sac.